SUBSCRIBE for Upcoming Course Announcements
Test yourself with this week’s ECG case. Then scroll down for a structured step-by-step interpretation and clinical pearl.
A 90 year old presented with epigastric pain and weakness.
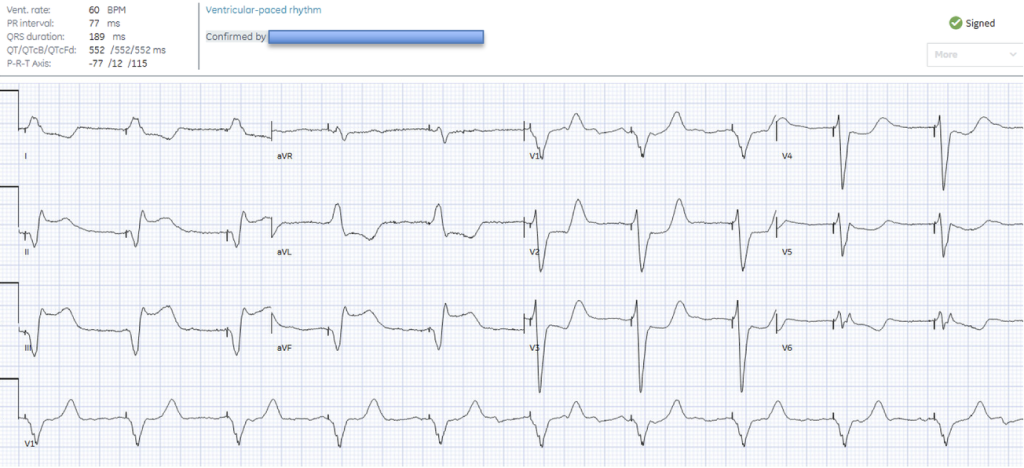
The final ECG interpretation is ventricular-paced rhythm. Is there anything else that could explain the patient’s symptoms?
Heart rate/rhythm: AF with ventricular pacing and capture
Electrical conduction: wide QRS with LBBB morphology, which should produce discordant and proportional STD
Axis: left axis
R-wave: late R wave
Tall/small voltages: normal
ST/T: excessive discordant STE inferior with reciprocal excessive STD in aVL, and concordant STD V2-4
infero-posterior occlusion MI. Cath lab activated: 100% LCX occlusion
1. It’s typical for elderly patients with acute coronary syndrome to present with anginal equivalents (eg weakness, dyspnea, epigastric pain, nausea) rather than chest pain
2. The Smith-Modified Sgarbossa criteria (concordant STE, concordant STD anteriorly, or excessive discordant STE/S>25%) can identify Occlusion MI in the presence of ventricular-paced rhythm.